Healthcare OS · Risk Stratification
Risk scores you can defend and act on.
IASORA scores every patient across 34 factors, shows the weight and source behind each one, proves its accuracy on your own history before go-live, and turns each risk level into governed clinical action.
0.75 to 0.80 AUROC on 30-day readmission · validated on your population before go-live · every factor traceable
A score nobody can explain is a score no clinician will act on and no board will sign off.
Platform sequence
From score to coordinated care.
Four steps on one record, none of them a batch job.
Ingest the record
Conditions, medications, labs, vitals, encounters, care gaps and utilisation in one longitudinal record per patient.
Score the patient
A 0 to 100 composite across four weighted risk areas, from a deterministic baseline, established clinical indices and a governed learned layer.
Explain the number
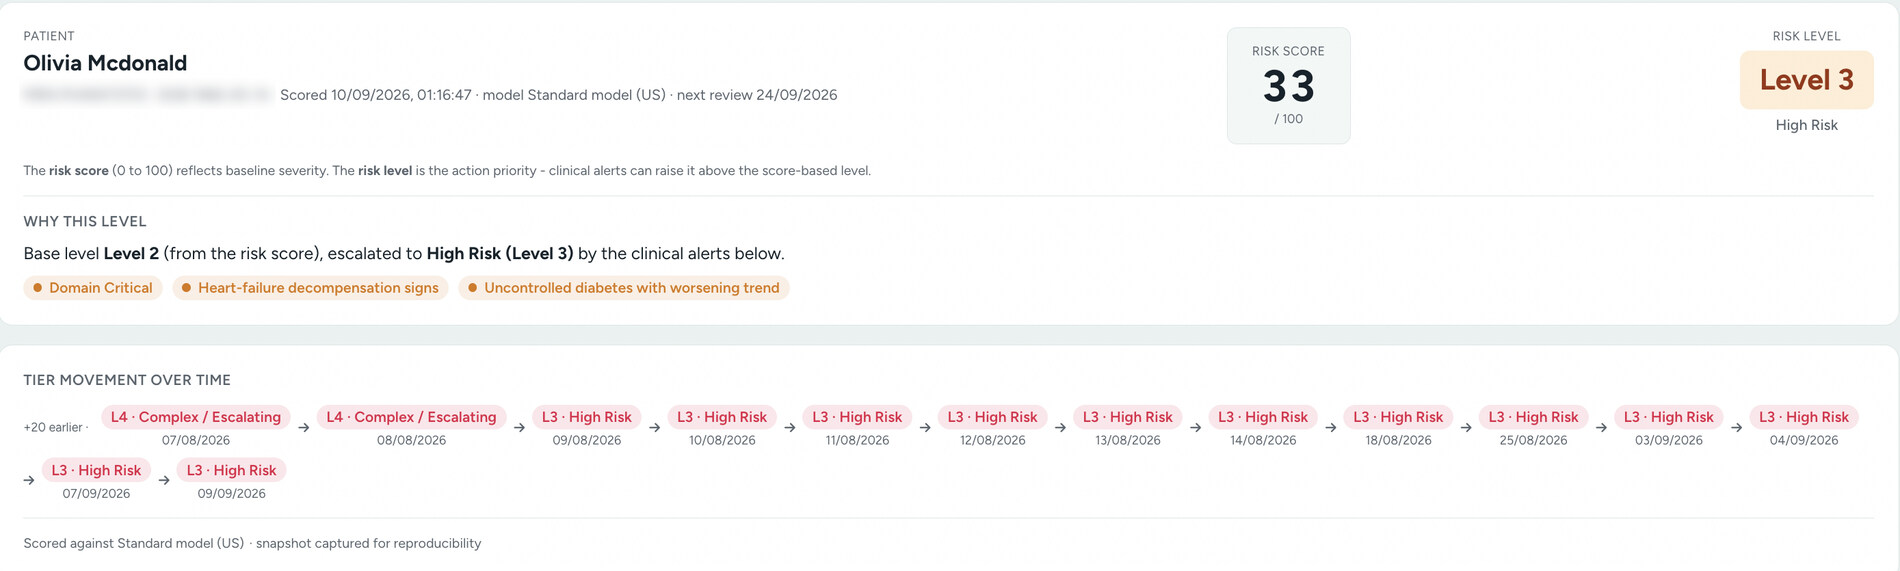
Every point traces to its factor, weight and data source, with tier changes over time and clinical triggers in plain language.
Trigger the care
Risk levels map to action queues. Outreach starts, response windows are enforced, and anything unanswered escalates to a care manager.
Population view
Your whole panel, stratified and current.
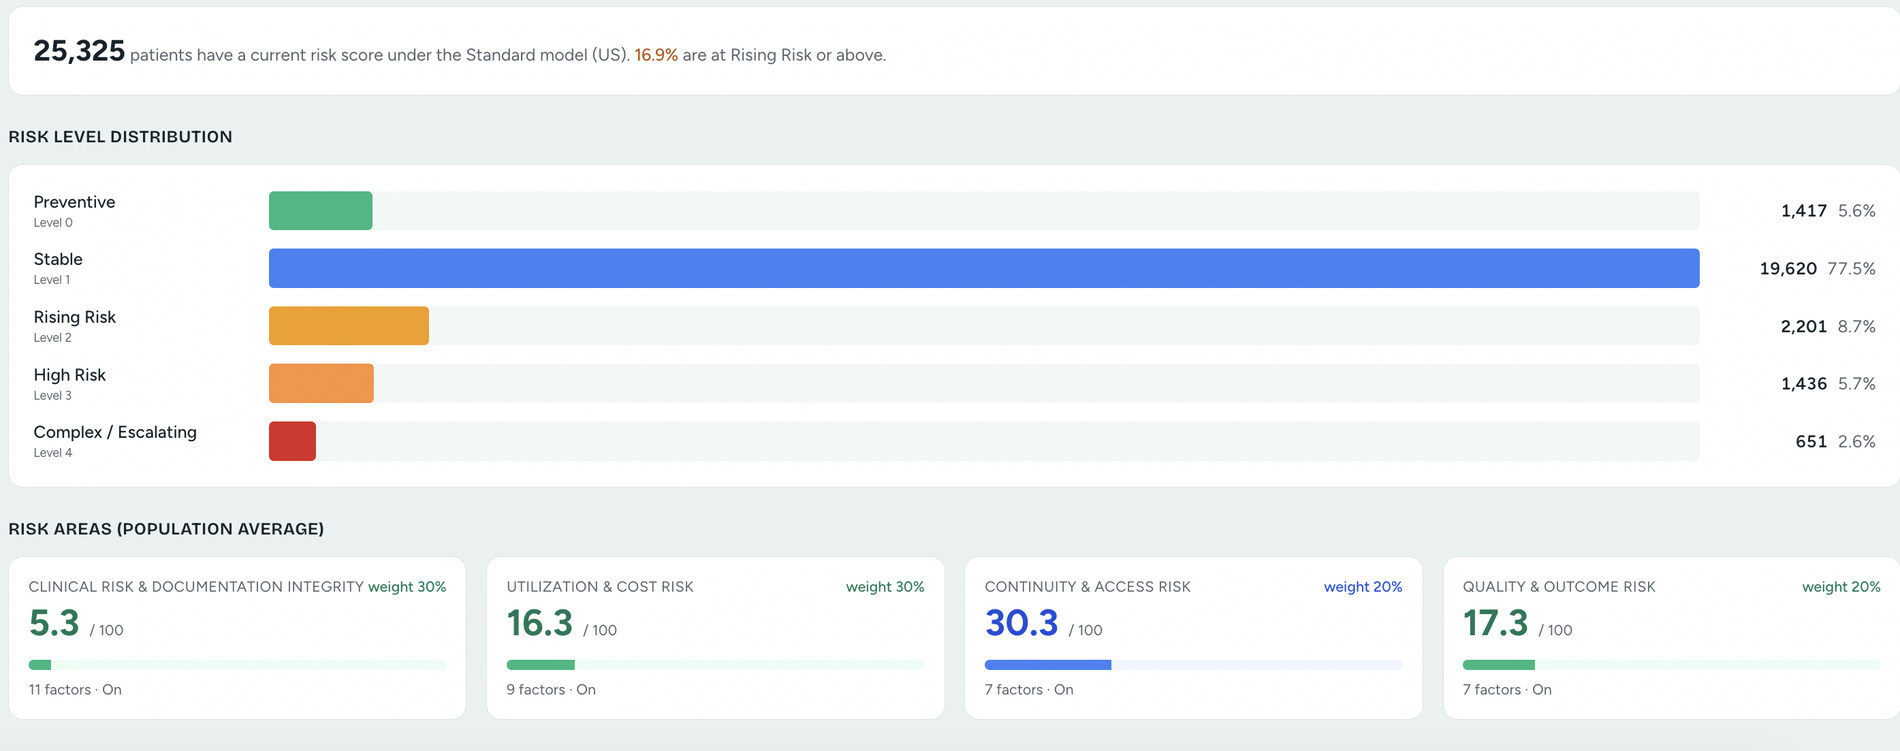
Glass-box architecture
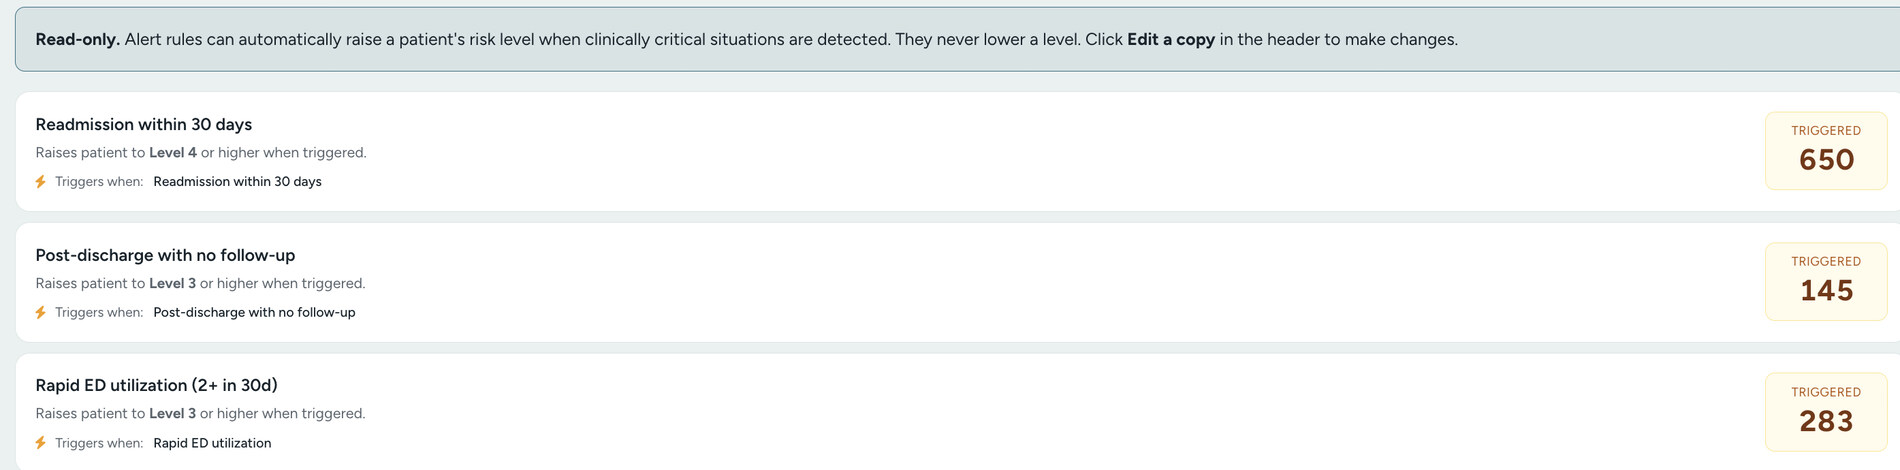
Every weight visible. Alerts only raise priority.
Four weighted risk areas, 34 factors, one composite. Clinical alert rules can raise a patient's action priority but never lower it, so a settled history cannot average away an acute event.
The score is baseline severity; the level is action priority. Keeping them apart lets a readmission or a missed post-discharge follow-up raise a patient today without rewriting a score the readmission has not yet earned.
In the product
The rule, and the patient it moved.
Operational impact
The score triggered the care.
Platform capabilities
Built to survive clinical, actuarial and board review.
Transparent 34-factor engine
Four weighted risk areas, 34 factors, one 0 to 100 composite.
Established clinical indices
NEWS2, heart failure risk, CHA₂DS₂-VASc, eGFR on CKD-EPI 2021, Wells DVT and Morse Fall, alongside Charlson, Elixhauser, HHS-HCC, LACE and NHS eFrailty.
External model adapters
Connect a third-party or proprietary scoring engine, including ACG-compatible endpoints, without custom integration work.
Governed learned layer
An optional learned adjustment, promoted only after accuracy, calibration, time-split and fairness checks pass. Reversible in one step.
Continuous re-scoring
Scores recalculate as ADT feeds, results and encounters land. No nightly batch.
Versioned model governance
Read-only standard models with tenant-tuned copies. Every weight, threshold and alert rule change is versioned with an audit diff.
Proven accuracy
Validated on your historical data before deployment.
Calibration and accuracy are proven on your own retrospective data before any production workflow goes live. Three outcomes are measured.
AUROC measures how well a model separates higher-risk from lower-risk patients: 0.5 is a coin toss, 1.0 is perfect. IASORA scores 0.75 to 0.80 on 30-day readmission in retrospective evaluation across a 323,000-patient history. Yours is measured the same way, on your population, before go-live.
Implementation
A risk score you can defend at the board and in the clinic.
Bring a cohort and a year of history. We validate the engine on your data before go-live, then show how each risk level becomes governed clinical action.